



I posted on this in one other thread.
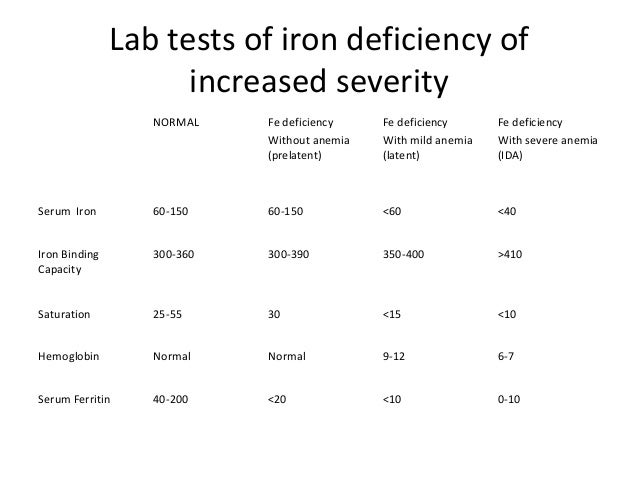
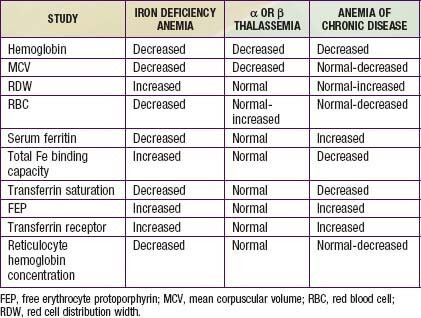
Transferring aim posts for anemia, and iron poor anemia medical definitions. Usually wanting on the totality of my intervention, low iron, low ferritin, low saturation, low hemoglobin, low MCV, excessive RDW. These are all at/close to anemic ranges.
My Aug 3, labs, I used to be clinically iron poor anemia.
Until you might have been donating blood repeatedly and/or have very low iron markers, in sick well being, and plan to take excessive dose rapamycin, I wouldn’t fear an excessive amount of about iron. However after all, it’s a must to monitor every part on rapamycin. If I had continued donating blood on my regular historic 8 week cycle throughout this excessive dose intervention, my iron would have tanked a lot decrease (I used to be close to medical anemia BEFORE beginning the intervention), and would have been very attention-grabbing to look at if I remained asymptomatic. Simply helps my thesis…fashionable meat consuming people have WAY extra iron saved in tissue than blood markers elucidate (extra iron is professional getting old). The reference values are far too excessive. 99% of the inhabitants has FAR greater iron shops than me, but I’m asymptomatic. However I’ve been adapting to dumping iron for over 5 years and a excessive endurance exerciser re O2 effectivity…so I’m seemingly not a standard iron physiological reference.
Ferritin is a comparatively poor marker. I’d concentrate on iron plasma, hemoglobin, saturation and your CBC. Don’t overlook to check sirolimus trough at each panel.

3 Likes
@MAC You might be superior.  Thanks for all of this.
What are your ideas concerning the potential for mTOR2 inhibition?

